CTN 222: Canadian co-infection cohort
Examining the effect of antiretroviral therapy (ART) on liver disease progression in people living with both HIV and hepatitis C virus (HCV)

About The Study
For over 20 years, Dr. Marina Klein’s Canadian Coinfection Cohort (CTN 222) has been one of the largest cohorts worldwide following adults living with HIV and living with or cured of hepatitis C. The cohort has documented the hepatitis C treatment revolution, from interferon-based therapies to the advent of the highly successful direct-acting antivirals (DAAs), providing critical evidence on treatment outcomes. With treatment now widely available, the cohort is looking beyond cure to examine the long-term consequences of a past hepatitis C infection on future health and wellbeing.
CTN 222 was the first observational cohort study approved by the CTN. Starting in 2002 in Montreal, the cohort now recruits at 17 sites across British Columbia, Alberta, Saskatchewan, Ontario, Quebec and Nova Scotia. Funding from the CTN and CIHR (2007, 2009, 2011, 2015, 2020, 2023) has allowed the cohort to recruit over 2091 people living with HIV and hepatitis C and, of these, 576 attended follow up visits in 2025.
Learn MoreBackground
Hepatitis C is an infection caused by the hepatitis C virus (HCV). The virus leads to inflammation and damage to the liver. HCV can be contracted through the same routes as HIV (mostly blood-to-blood contact or sexual contact). It is estimated that 20–30% of Canadians living with HIV also have HCV. Coinfection with HIV increases HCV viral replication and accelerates the progression of liver disease. In Canada, there are approximately 214,000 Canadians living with HCV, 70,900 Canadians living with HIV, and 14–21,000 Canadians living with both HCV and HIV. HIV–HCV co-infection is a major public health concern that disproportionately affects social and structurally vulnerable populations. This includes individuals facing poverty, unstable housing, substance use, stigma, discrimination, and barriers to accessing healthcare.
Research using cohort data has evolved from studying liver disease progression to the success rates and uptake of new DAA treatments, and to the risk of re-infection. The next phase of our research is to understand the long-term health consequences of a past HCV infection, including the risk of steatotic liver disease, diabetes, and cardiovascular disease. As people living with HIV age, these comorbidities are far more prevalent than in the general population. There is evidence that a prior HCV infection results in permanent immunologic damage and this may increase comorbidity risks for those with a past HCV infection. An increased risk would imply those with a past HCV infection need early or more frequent fatty liver disease monitoring, diabetes screening, and primary CVD prevention than is currently recommended for those living with HIV.
Study Approach
CTN 222 is a long-term observational cohort study and its participants are a diverse group of people linked to care including men who have sex with men (MSM), current and ex-injection drug users, Indigenous peoples, and women. Our participants are similar to those found in Canadian population studies of those with HIV and HCV (the BC Hepatitis Testers Cohort and PHAC I-Track surveys).
All eligible individuals who visit a cohort clinic are invited to participate in the study. Those enrolled are seen every 6 months at follow-up visits linked to their routine clinical care during which they complete a questionnaire, undergo a liver fibroscan, and provide clinical and research blood samples. Sociodemographic, behavioural and clinical data are collected, including information on diagnoses, HIV and HCV treatment, and care received.
Results
Since its inception, CTN 222 has led to 97 peer-reviewed publications: 23 papers published before 2015, 27 papers published between 2015 and 2019, and 47 papers published since 2020. The cohort has evolved from studies of disease progression and treatment outcomes to research on HCV elimination and long-term health. This sustained output has made the cohort an internationally recognized platform for understanding HIV–HCV coinfection and informing clinical care and policy.
Before 2015, our research focused on defining the natural history of HIV–HCV coinfection. Major themes included liver fibrosis progression, mortality, immune dysfunction, treatment outcomes with interferon-based therapies, genetic and immunological determinants of disease, and the impact of antiretroviral therapy on liver-related health. From 2015–2020, the research program evolved to address the transition to DAA therapy. Investigators evaluated treatment uptake, barriers to treatment, quality of life, reinfection, mortality trends, and the effects of policy changes on treatment access. During this period, the cohort also became a leading source of evidence on social determinants of health, including food insecurity, incarceration, substance use, and depression.
Since 2020, research has increasingly focused on HCV elimination, engagement in care, transmission risk, long-term outcomes after cure, hepatic steatosis, use of health services, overdose mortality, and mental health. New studies have examined COVID-19, virtual care, vaccine responses, and progress toward national elimination goals, while continuing to identify gaps in prevention and care among priority populations.
The cohort has also made important contributions to epidemiological and statistical methodology. Investigators have developed and applied dynamic treatment regime models, Bayesian and semiparametric causal inference methods, measurement error correction techniques, and methods for evaluating health policy interventions. These methodological studies have influenced research beyond HIV and viral hepatitis.
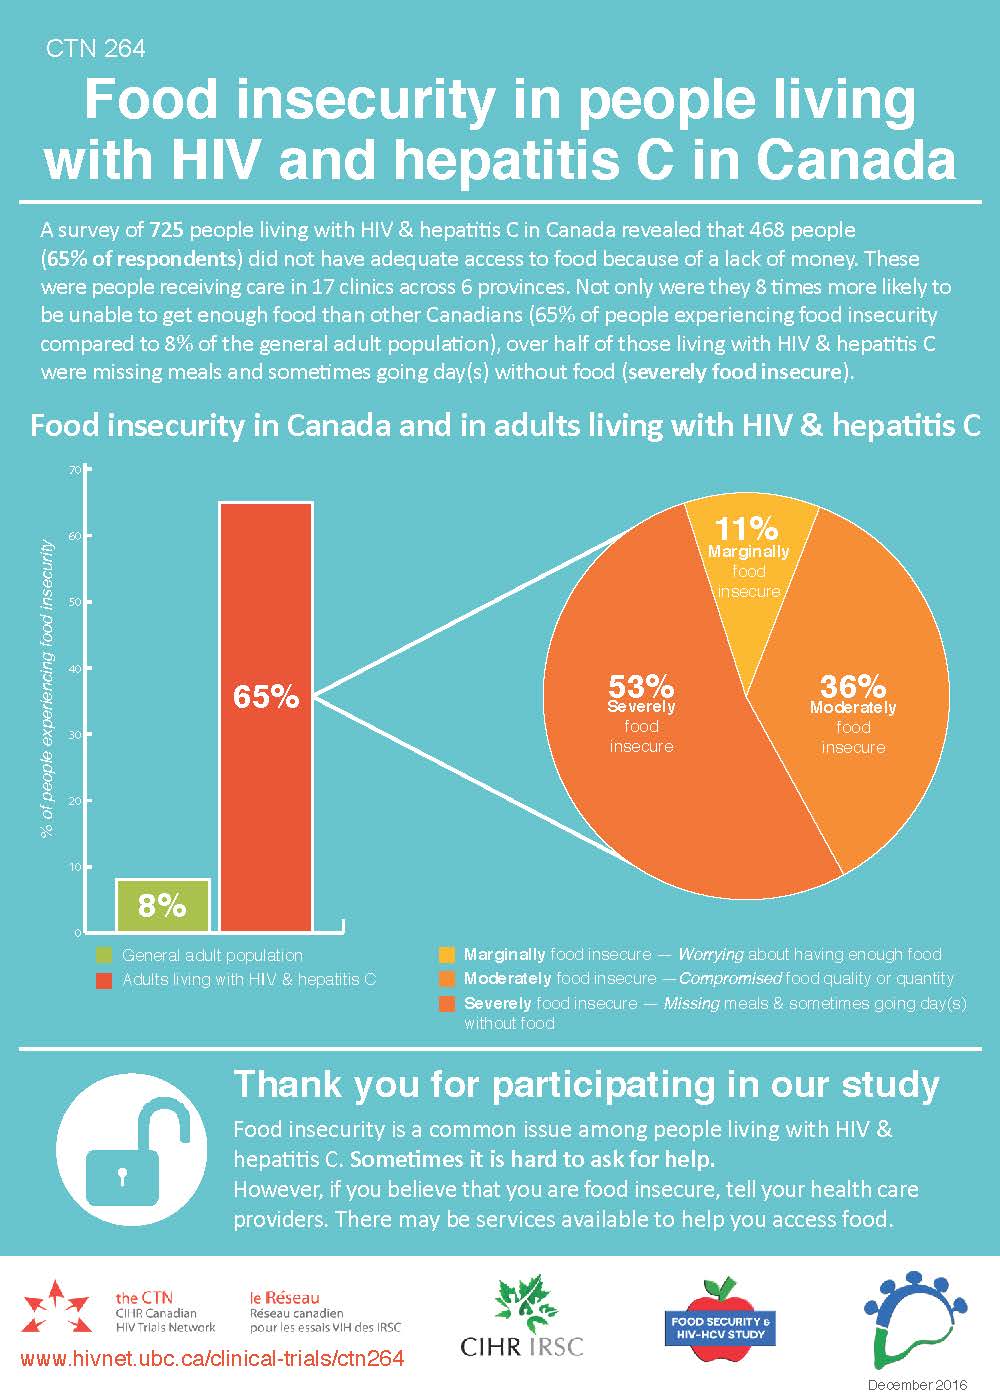
The cohort is used as a platform for other studies. These have included a study on food insecurity (CTN 264) and interventional trials at cohort sites – on citalopram as a treatment for depression (CTN 194), raltegravir as an alternative to protease inhibitors in HIV treatment (CTN 260), and switching to a single tablet treatment for HIV to improve treatment adherence (CTN 286).
Additional Information
You can contact the CTN 222 team via email at cviscoco@gmail.com and on X at our handle @cocostudy.
Background
HCV is a virus that attacks the liver, causing liver disease (hepatitis). Because HCV can be contracted through the same routes as HIV (blood-to-blood contact, sexual contact, etc.) over 30% of people living with HIV worldwide also have HCV. Due to the success of antiretroviral therapies (ART), complications from comorbidities such as HCV have replaced AIDS-related infections as the primary health concern among people living with HIV.
End-stage liver disease (ESLD) due to HCV is one of the leading causes of illness and death in HIV/HCV+ people. The natural course of HCV is accelerated in people living with HIV. Initially, the ability of ART to restore the immune system was expected to improve liver health in this population. This was not the case, however, and liver disease continues to be a significant problem. In response, CTN 222 was formed to document and understand the social and biological factors that contribute to the interaction between these two viruses and their treatment and management.
Study Approach
CTN 222 is a long-term observational cohort study and includes a diverse group of people including men who have sex with men (MSM), current and ex-injection drug users, Indigenous people, and women. All eligible individuals who visit a participating clinic are invited to participate in the study. Those who initially decline the invitation are eligible to enrol in the future.
After giving informed consent and undergoing an initial evaluation, CTN 222 participants return approximately every 6 months, either as a part of clinical care or for study purposes alone. Clinical, sociodemographic, behavioural, medical, and treatment information is collected. Treatment and diagnosis history is also collected from past medical visits.
Knowledge Mobilization
Impact
Publications from this study have been cited and used to inform policy and care decisions across the world — below are a few key examples of this reach and impact.

Guidelines for the screening, care and treatment of persons with hepatitis C infection
World Health Organization
Guidelines for the use of antiretroviral agents in HIV-1-infected adults and adolescents
Centre for Disease Control (CDC)
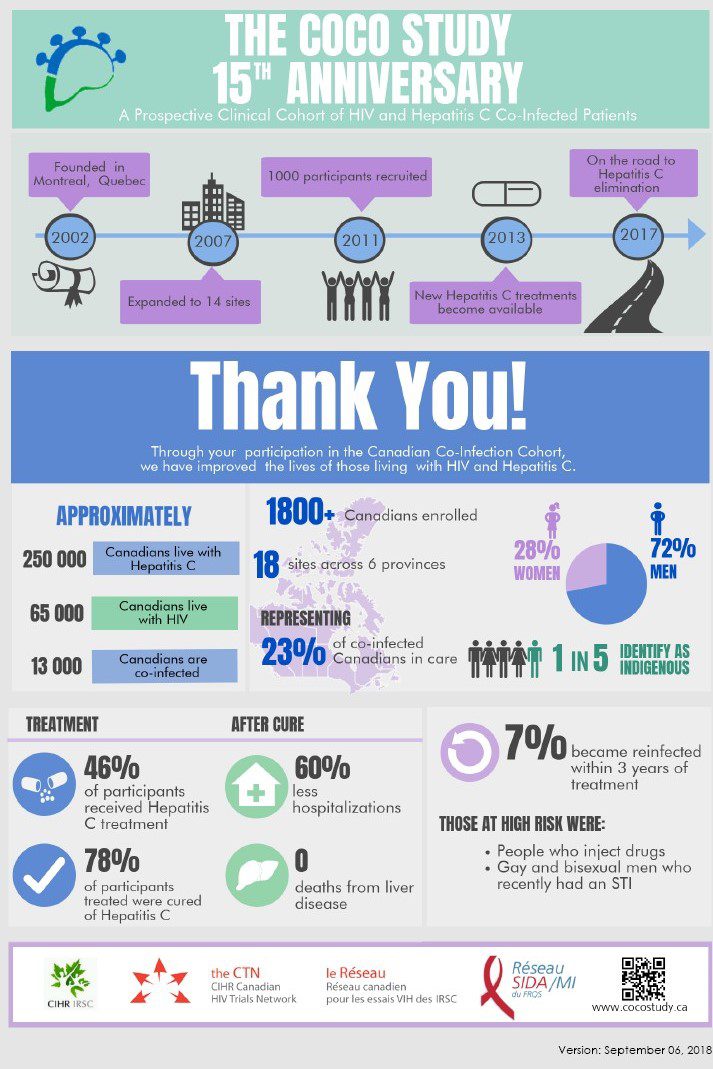
Infographics
You can download the infographics related to the study here.


Key Clinical Papers
Discover 11 key clinical papers related to the study below.
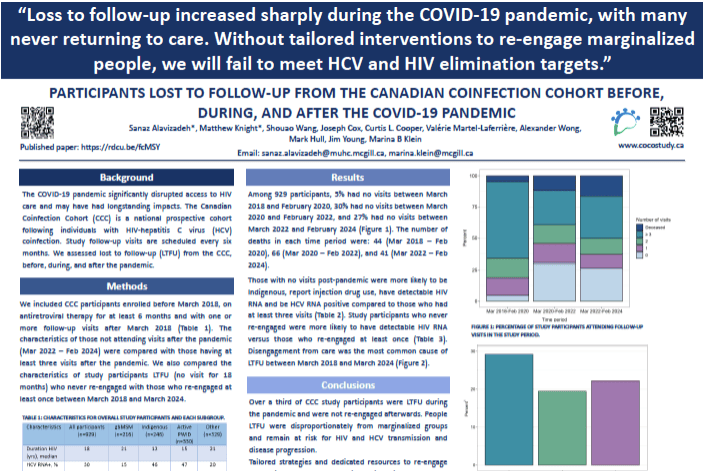
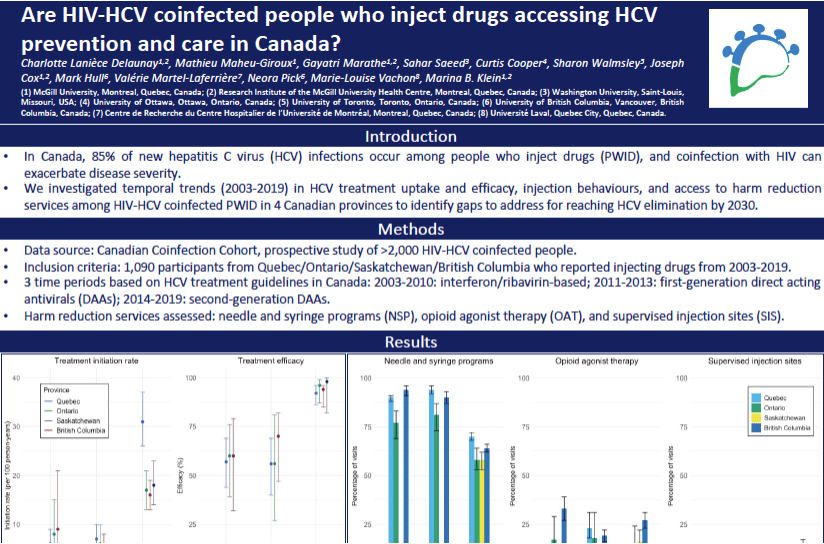
Gaps in hepatitis C virus prevention and care for HIV-hepatitis C virus co-infected people who inject drugs in Canada
International Journal of Drug Policy
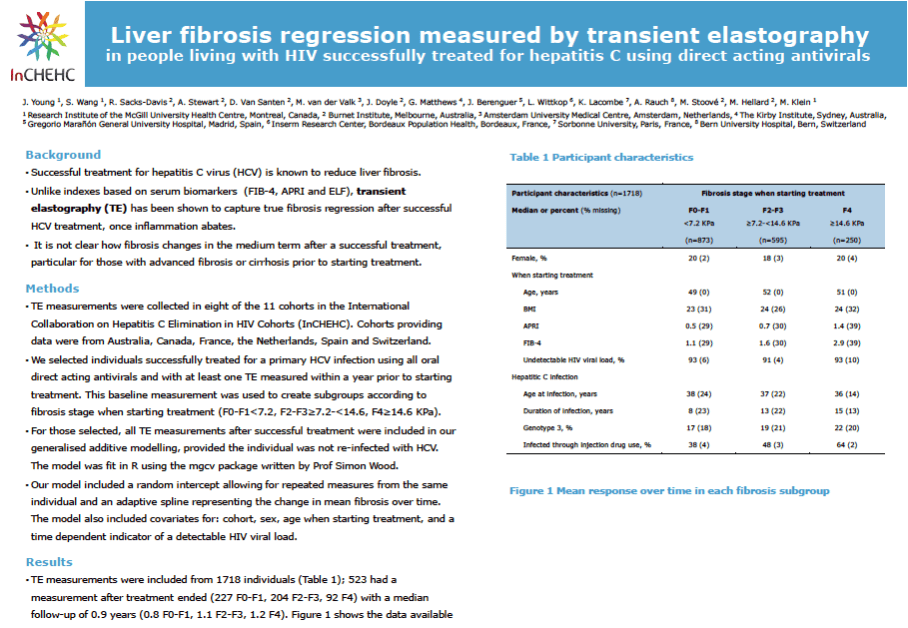
Liver Fibrosis Regression in People Living With HIV After Successful Treatment for Hepatitis C
Journal of Acquired Immune Deficiency Syndromes
Changes in Hepatic Steatosis Before and After Direct-Acting Antiviral Treatment in People With HIV and Hepatitis C Coinfection
The Journal of Infectious Diseases
Do contemporary antiretrovirals increase the risk of end-stage liver disease? Signals from patients starting therapy in the NA-ACCORD
Pharmacoepidemiology & Drug Safety
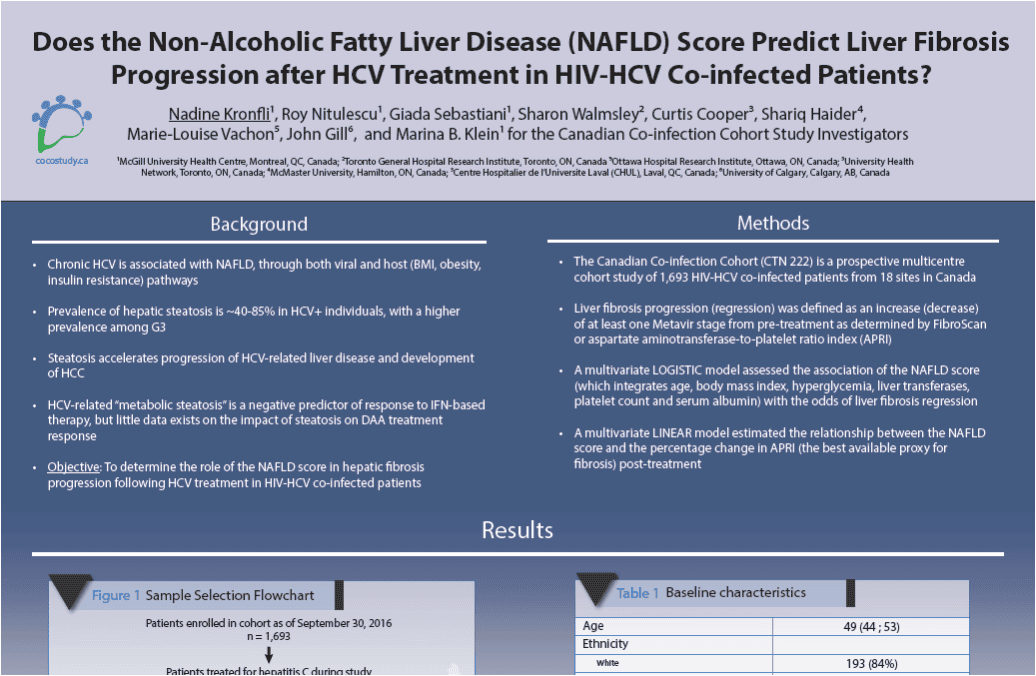
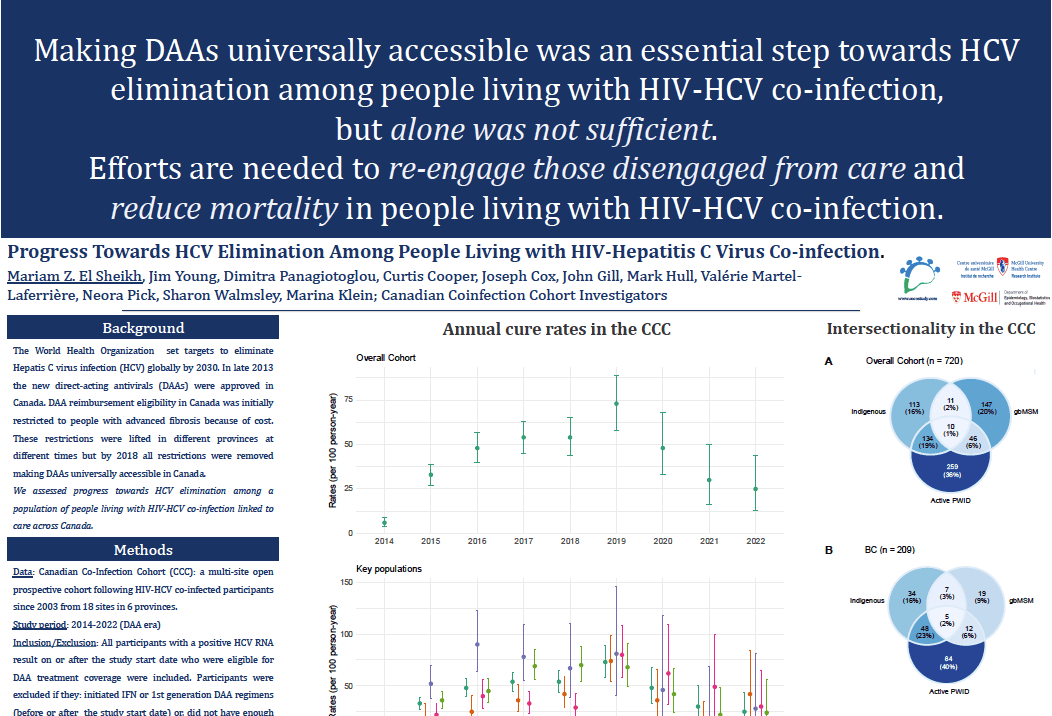
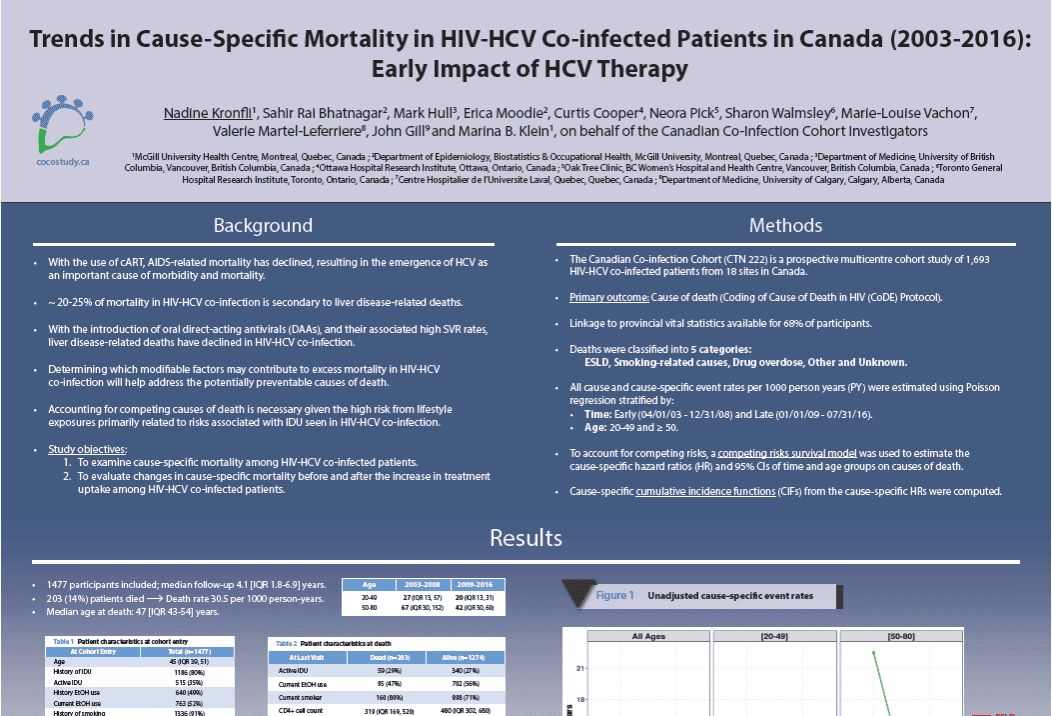
Posters
You can download a core selection of posters related to the study here.
Key Methods Papers
Discover six key methods papers related to the study below.
Predicting the presence of depressive symptoms in the HIV‑HCV co‑infected population in Canada using supervised machine learning
BMC Medical Research Methodology
The Impact of Sparse Follow-up on Marginal Structural Models for
Time-to-Event Data
American Journal of Epidemiology
Segmented generalized mixed effect models to evaluate health outcomes
International Journal of Public Health
Evaluating the impact of health policies: using a difference-indifferences approach
International Journal of Public Health
Comparing direct acting antivirals for hepatitis C using observational data – Why and how?
Pharmacology Research & Perspectives
Eligibility Requirements & Procedures
Eligibility
- Aged 16 years or older (or consistent with provincial guidelines)
- Documented HIV seropositive infection
- Documented HCV infection or evidence of exposure
- Able to provide informed consent
l
l
l
l
l
l
l
l
l
l
Study Procedures
Mandatory Assessments (every 6 months)
- Questionnaire
- Standard of care blood collection
-
Vital signs
- Height (record once at baseline)
-
Weight, waist, blood pressure
-
- ,
-
Site-Specific Assessment (annually, if fibroscan is available)
-
Fibroscan
- ll
Optional Assessment
-
Research blood collection
- Serum and plasma (every 6 months)
-
PBMC (collect at baseline and DAA visits)
Compensation
-
$25 per visit for time and travel